
Opinion|Videos|June 11, 2025
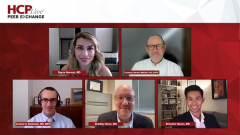
Balancing Complement Inhibition and Infection Risk in C3G Treatment
Panelists discuss how patient history, vaccination status, and risk of infection influence the decision to administer complement inhibitors, with some expressing caution in high-risk cases, particularly in pediatric populations with prior infections or low immunoglobulin levels.
Advertisement
Video content above is prompted by the following:
Summary for Physicians on Use of Complement Inhibitors in High-Risk Patients:
Identifying High-Risk Patients:
- Patients with nephrotic syndrome who experience significant protein loss, leading to very low IgG levels, are at an increased risk for infections. These patients may not be ideal candidates for complement inhibitors due to concerns about their ability to fight bacterial infections, particularly encapsulated organisms.
Risk of Infections and Safety Concerns:
- Early trial data, particularly from studies like VALIANT and APEX, suggest that while complement inhibitors are used in posttransplant patients on immunosuppressive therapy, they did not significantly increase the risk of infections, especially when vaccinated and managed with prophylactic antibiotics.
- Vaccination and prophylactic antibiotics (e.g., penicillin or macrolides) are essential to reduce infection risks when using complement inhibitors. It’s important to assess local infection resistance patterns (e.g., penicillin resistance rates) before initiating therapy.
Exclusion Criteria in Clinical Trials:
- Clinical trials, such as the APEX trial, excluded patients with a history of recurrent invasive infections caused by encapsulated organisms. However, in clinical practice, the timing of infections, vaccination status, and use of prophylactic antibiotics are important factors to consider.
- A patient who has had a meningococcal infection but was not vaccinated may still be a candidate for complement inhibitor therapy if vaccinations are administered and prophylactic antibiotics are used.
Pathways to Safe Use:
- In real-world settings, physicians may proceed with complement inhibitors in high-risk patients, provided that adequate precautions are taken, including vaccination, use of prophylactic antibiotics, and consultation with infectious disease specialists when necessary. This approach has been successful in managing patients safely over extended periods.
Patient and Parental Concerns:
- It’s crucial to address concerns from parents or caregivers, particularly in pediatric populations. Parents need reassurance regarding the safety of long-term use of complement inhibitors, especially in the context of infection risks.
Advertisement
Related to this article

Nephrology in September 2026: FDA approves finerenone for CKD in T1D and obinutuzumab for nephrotic syndrome, plus ORIGIN 3 IgAN data.

Nephrology in Q3 2026: FDA approvals for atacicept, iptacopan, finerenone, and obinutuzumab, plus 2-year IgAN data and CKD screening.

Q3 2026 dermatology recap: FDA approvals in dermatomyositis, adolescent alopecia areata, and sBCC, plus new psoriasis and vitiligo findings.
Approved US PFIC drugs treat pruritus. The researcher behind a therapy targeting BSEP on diagnosis, data, and what comes next.
Florence Schleich, MD, PhD, explains how exacerbation phenotypes and useful biomarkers shift across anti-IL-5, anti-IL-5R, and anti-TSLP therapies.

Hematology in September 2026: ASH raises ferritin thresholds for iron deficiency, plus marstacimab in hemophilia and curative SCD care.
Strong recommendations cover carvedilol or banding for varices, semiannual HCC surveillance, vaccines, and smoking cessation.
April Armstrong, MD, MPH, discusses 1-year RELIEVE-AD-PEDs data on rapid, sustained dupilumab disease control in adolescents with atopic dermatitis.
Advertisement
Advertisement
Trending on HCPLive
1
RELIEVE-AD-PEDs: Dupilumab Sustains Adolescent Atopic Dermatitis Control at 1 Year
2
Conservative Therapy in Fibrillary GN: A Four-Drug Kidney-Protective Approach
3
The Benefits and Limits of Enlicitide, With Ninel Hovnanians, MD
4
Top Reason for Leaving HAE Attacks Untreated, Survey Finds
5